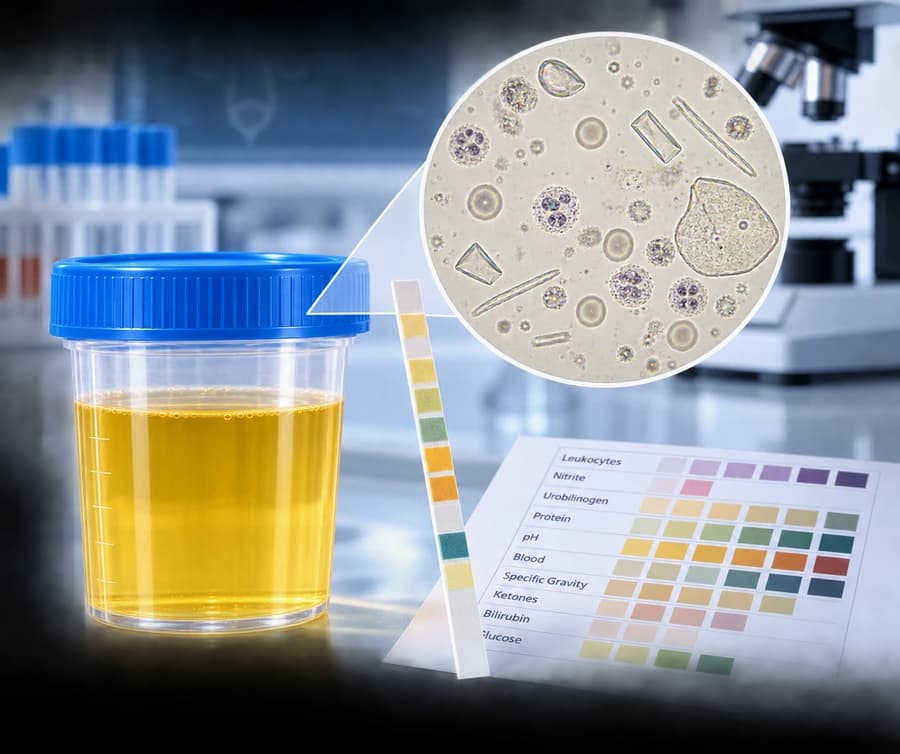
The 3 levels of urinalysis — and why it is not a diagnosis
Urinalysis is not one test but three, performed together:
- Macroscopic assessment: appearance, color, cloudiness, odor
- Chemical dipstick analysis: pH, specific gravity, protein, glucose, ketones, nitrites, leukocyte esterase, blood, bilirubin, urobilinogen
- Microscopic examination of the sediment: white blood cells (WBC), red blood cells (RBC), casts, crystals, bacteria, epithelial cells, yeast
Its role is screening/triage: it shows *who* needs further, targeted testing, not *what* the final diagnosis is. An abnormal finding always needs to be correlated with symptoms, history, and — where relevant — a confirmatory test.
Macroscopic check
A first, non-specific impression (e.g. cloudy urine or a color change) — never a stand-alone diagnosis.
Dipstick chemical analysis
A fast, semi-quantitative check of multiple parameters — high sensitivity, limited specificity.
Sediment microscopy
Direct visualization of cells/crystals — more specific, but still needs clinical correlation.
When it is requested and how it is used
Main indications:
- symptoms suggestive of a urinary tract infection (dysuria, frequency, urgency)
- investigation of blood in the urine
- monitoring known kidney disease or diabetes
- general preventive or pre-operative screening
It acts as a screening tool: it determines *who* needs a culture, imaging, ACR/PCR testing, or a nephrology referral — not *what disease* someone has with certainty.
Correct sample collection (per EFLM guidance)
The reliability of the result depends heavily on collection technique:
- a midstream sample is preferred — different from the very first part of voiding
- local cleaning beforehand, without routine use of antiseptic solutions (these can alter the sample)
- a first-morning sample is preferred for microscopy/specific gravity, but a random sample is acceptable for most routine testing
- a sterile container and prompt delivery to the laboratory — there is no rigid "2-hour rule": leaving the sample at room temperature progressively reduces reliability, particularly for cells and bacteria
Poor collection or delayed processing are among the most common causes of false-positive or false-negative results.
White cells, esterase, and nitrites — pyuria ≠ automatic infection
Important clarifications:
- positive leukocyte esterase or elevated WBC (pyuria) does not automatically mean a urinary infection — it can reflect inflammation without active infection, sample contamination, or another cause
- negative nitrites do not rule out infection: several UTI-causing organisms (e.g. Enterococcus, Staphylococcus saprophyticus) do not produce nitrites, and urine needs to remain in the bladder long enough for nitrites to be detectable
- the combination of WBC + nitrites + symptoms significantly raises the likelihood of a bacterial infection, but final confirmation comes from a urine culture
Interpretation is always done together with symptoms, never in isolation.
Sterile pyuria
WBC+ with a negative culture — warrants a search for another cause (e.g. stones, inflammation, incompletely treated infection).
Likely urinary infection
Positive WBC/nitrites with compatible symptoms — usually justifies a culture before antibiotics.
Asymptomatic bacteriuria
Bacteria without symptoms — in most adults this does not require treatment, aside from specific exceptions.
Bacteria on urinalysis vs urine culture — two different tests
Urinalysis does not replace a urine culture:
- urinalysis gives a qualitative/semi-quantitative indication of bacteria, without identifying the organism or providing an antibiogram
- the urine culture is the reference test for confirming infection, identifying the pathogen, and guiding targeted antibiotic therapy
- bacteria on urinalysis without symptoms often represent asymptomatic bacteriuria or sample contamination, not disease requiring treatment
The assumption "positive urinalysis = infection that needs antibiotics" is one of the most common causes of unnecessary antibiotic use.
Dipstick blood vs confirmed microscopic hematuria
A positive dipstick for blood is not equivalent to confirmed microscopic hematuria:
- the dipstick detects hemoglobin/myoglobin through a chemical reaction — it can give a false-positive result due to menstruation, vigorous exercise, dehydration, or certain medications
- per the AUA/SUFU (2025 Amendment) guideline, confirmed microscopic hematuria is defined as ≥3 red blood cells per high-power field (RBC/HPF) on a properly collected, centrifuged sample — not simply a positive dipstick
- anticoagulant therapy does not, by itself, explain persistent hematuria and should not automatically be assumed to be the cause — the same work-up is still required
Persistent, confirmed microscopic hematuria needs a structured work-up to rule out stones, a tumor, or another significant cause.
Positive dipstick, normal microscopy
Likely false-positive (menstruation, exercise, dehydration) — often warrants repeat testing under proper conditions.
Confirmed microscopic hematuria
≥3 RBC/HPF on a properly collected sample — warrants a structured work-up based on age/risk factors.
Gross (visible) hematuria
Blood visible to the naked eye — always needs prompt urological assessment, regardless of dipstick findings.
Dipstick protein vs quantified albuminuria (ACR/PCR)
A positive dipstick for protein is not equivalent to quantified albuminuria:
- the dipstick mainly detects albumin, is semi-quantitative, and is affected by how concentrated the urine is
- per the KDIGO 2024 Clinical Practice Guideline, quantification is done using the urine albumin-to-creatinine ratio (ACR) or, alternatively, the protein-to-creatinine ratio (PCR) — not the semi-quantitative dipstick
- the combination of protein + blood, or protein + casts, raises the likelihood of kidney (rather than purely urological) involvement, and often leads to a creatinine check and nephrology evaluation
An isolated, mild proteinuria finding on a single test, with no other abnormalities, is often transient and can simply be repeated.
Crystals, pH, and specific gravity — crystals ≠ stones
Crystals on urinalysis do not automatically mean you have kidney or bladder stones:
- calcium oxalate, uric acid, or phosphate crystals can also appear in healthy people, especially when the sample sits or is refrigerated before microscopy
- urine pH gives an indirect clue about susceptibility to certain stone types (e.g. acidic pH → uric acid stones), but does not, by itself, confirm stone disease
- confirming kidney stones or bladder stones requires imaging, not a crystal finding on urinalysis
- specific gravity reflects urine concentration/hydration status and helps interpret other parameters, without being diagnostic on its own
Glucose, ketones, bilirubin, and urobilinogen
Metabolic findings that need careful interpretation:
- glucosuria is usually linked to hyperglycemia, but it does not always mean poorly controlled diabetes — SGLT2 inhibitors deliberately cause glucosuria as part of their mechanism of action, without this reflecting poor control
- ketones can appear with prolonged fasting, a low-carbohydrate intake, or inadequately controlled diabetes — the clinical picture determines the severity
- abnormal bilirubin/urobilinogen relate to hepatobiliary causes, not a primary urological condition
These findings usually point toward internal-medicine, endocrine, or gastroenterology evaluation, not a urological intervention.
Casts, epithelial cells, yeast, and sample contamination
Other microscopic findings:
- casts (hyaline, granular, red or white cell casts) form in the renal tubules — red cell or granular casts significantly raise suspicion of a kidney (glomerular) cause
- large numbers of squamous epithelial cells usually indicate contamination from skin/mucosa, not disease
- yeast (most often Candida) can reflect colonization, especially in catheterized or immunosuppressed patients, rather than active infection requiring treatment
- signs of contamination (multiple bacterial species together with abundant squamous cells) reduce the reliability of the sample and often warrant repeat testing with correct technique
Which test answers which question — three common patient journeys
Urinalysis is the first step, not the last:
- "Is there an active infection?" → urinalysis (WBC, esterase, nitrites) → if positive/symptomatic → urine culture for identification and antibiogram
- "Is the blood real and significant?" → dipstick blood → microscopy to confirm (≥3 RBC/HPF) → if confirmed → imaging/cystoscopy as appropriate, see hematuria
- "Is the kidney involved?" → dipstick protein/blood → quantification with ACR/PCR → creatinine and nephrology evaluation where indicated
Each journey starts at urinalysis as the triage point, but the answer comes from the next, targeted test.
Confusing scenarios — what the findings actually mean
Common misunderstandings based on real findings:
- "Bacteria positive, no discomfort at all": often asymptomatic bacteriuria — in most adults this does not need antibiotics
- "WBC positive, culture negative": "sterile pyuria" — warrants a search for another cause (e.g. an incompletely treated infection, inflammation, rarely urinary tract TB)
- "Blood positive, no RBC on microscopy": likely a false-positive dipstick (hemoglobin/myoglobin, medications, concentrated urine) — does not confirm hematuria
- "Protein positive just once": an isolated finding, often transient (fever, vigorous exercise, orthostatic proteinuria) — worth repeating before further work-up
- "My urinalysis is normal": this does not rule out every urological problem — e.g. asymptomatic tumors, mild obstruction, or certain stone types can coexist with a normal urinalysis
Practical questions, special populations, and when to seek urgent evaluation
Practical clarifications:
- fasting is not usually required; medications should not be stopped without medical guidance just for this test
- during menstruation, it is preferable to postpone the test when possible, or to inform the laboratory so any blood finding is interpreted correctly
- significant dehydration or overhydration can alter specific gravity and semi-quantitative findings
- in pregnancy, mild glucosuria or trace protein may carry different clinical weight and need specialized obstetric/urological assessment
- in children and in patients with a long-term catheter, the thresholds for a positive finding and their clinical significance differ meaningfully from a typical adult
Seek prompt evaluation for: visible (gross) hematuria, fever with signs of a urinary infection, inability to urinate, or severe renal colic pain — regardless of the individual urinalysis findings.


